---
title: "Mutant CALR targeted Therapies"
subtitle: "A Comprehensive Review of the Emerging Therapeutic Landscape"
author: "Ashwin — Vanderbilt University Medical Center / Vanderbilt Ingram Cancer Center"
date: today
format:
html:
toc: true
toc-depth: 4
toc-location: right
number-sections: true
code-fold: true
code-summary: "Show code"
theme:
light: journal
dark: journal
smooth-scroll: true
fig-align: center
fig-responsive: true
mainfont: "Source Sans Pro"
monofont: "Fira Code"
fontsize: "1.05em"
linestretch: 1.6
link-external-newwindow: true
css: |
<style>
.callout-note { border-left-color: #2c7bb6; }
.callout-important { border-left-color: #d7191c; }
.callout-tip { border-left-color: #1a9641; }
h1 { color: #2c3e50; border-bottom: 2px solid #3498db; padding-bottom: 0.3em; }
h2 { color: #34495e; }
h3 { color: #7f8c8d; }
.gt_table { font-size: 0.9em; }
.quarto-title-block { background: linear-gradient(135deg, #1a1a2e 0%, #16213e 50%, #0f3460 100%); color: white; padding: 2em; border-radius: 10px; margin-bottom: 1.5em; }
.quarto-title-block .title { color: white; }
.quarto-title-block .subtitle { color: #a8d8ea; }
</style>
pdf:
toc: true
number-sections: true
geometry:
- top=25mm
- left=20mm
- right=20mm
- bottom=25mm
mainfont: "Source Sans Pro"
monofont: "Fira Code"
fontsize: 11pt
documentclass: article
colorlinks: true
execute:
echo: true
warning: false
message: false
cache: true
bibliography: references.bib
---
```{r}
#| label: setup
#| include: false
# Load R packages
library(dplyr)
library(tidyr)
library(ggplot2)
library(gt)
library(knitr)
# Set ggplot2 theme
theme_set(
theme_minimal(base_size = 13, base_family = "sans") +
theme(
plot.title = element_text(face = "bold", size = 15, color = "#2c3e50"),
plot.subtitle = element_text(size = 11, color = "#7f8c8d"),
panel.grid.minor = element_blank(),
legend.position = "bottom"
)
)
# Color palette
calr_colors <- c(
"Monoclonal Ab" = "#2c7bb6",
"T-Cell Engager" = "#d7191c",
"CAR-T" = "#fdae61",
"Vaccine" = "#1a9641",
"ADC" = "#abd9e9"
)
```
```{python}
#| label: python-setup
#| include: false
import pandas as pd
import numpy as np
```
# Introduction {#sec-intro}
Calreticulin (CALR) mutations represent the second most common driver mutation in BCR::ABL1-negative myeloproliferative neoplasms (MPNs), identified in approximately 25% of essential thrombocythemia (ET) and 35% of primary myelofibrosis (MF) cases. First described simultaneously by Klampfl *et al.* and Nangalia *et al.* in two seminal 2013 *New England Journal of Medicine* publications, these somatic mutations in exon 9 generate a shared 36-amino acid C-terminal neopeptide that drives oncogenic signaling through constitutive activation of the thrombopoietin receptor (MPL/TPOR).
::: {.callout-note}
## Why CALR Is an Ideal Immunotherapy Target
The mutant CALR neopeptide is:
1. **Tumor-specific** — Absent in normal tissues, expressed exclusively on the malignant clone
2. **Displayed on the cell surface** — Complexed with MPL, accessible to antibody-based therapies
3. **Required for oncogenicity** — Cannot be silenced without loss of fitness advantage
4. **Shared across patients** — The identical 36-aa neopeptide is present in all CALR-mutant MPNs
:::
Over the past decade, this biological vulnerability has catalyzed an unprecedented wave of therapeutic innovation. Multiple CALR-directed modalities are now in various stages of development, from preclinical validation to registrational trials. This document provides a comprehensive review of the current landscape.
## CALR Mutation Biology
```{python}
#| label: fig-calr-mutations
#| fig-cap: "Distribution of CALR mutation types in ET and MF"
import matplotlib.pyplot as plt
import matplotlib
matplotlib.rcParams['font.family'] = 'sans-serif'

categories = ['ET\n(N=51, INCA033989)', 'MF\n(N=59, INCA033989)', 'General MPN\nPopulation']
type1 = [55, 58, 50]
type2 = [29, 24, 30]
other = [16, 19, 20]

x = np.arange(len(categories))
width = 0.25

fig, ax = plt.subplots(figsize=(9, 5))
bars1 = ax.bar(x - width, type1, width, label='Type 1 (52-bp del)', color='#2c7bb6', edgecolor='white', linewidth=0.8)
bars2 = ax.bar(x, type2, width, label='Type 2 (5-bp ins)', color='#d7191c', edgecolor='white', linewidth=0.8)
bars3 = ax.bar(x + width, other, width, label='Other', color='#fdae61', edgecolor='white', linewidth=0.8)

ax.set_ylabel('Percentage (%)', fontsize=12)
ax.set_title('CALR Mutation Type Distribution Across Cohorts', fontsize=14, fontweight='bold', pad=15)
ax.set_xticks(x)
ax.set_xticklabels(categories, fontsize=11)
ax.legend(frameon=True, facecolor='white', edgecolor='#cccccc', fontsize=10)
ax.set_ylim(0, 75)
ax.spines['top'].set_visible(False)
ax.spines['right'].set_visible(False)

for bars in [bars1, bars2, bars3]:
    for bar in bars:
        height = bar.get_height()
        ax.annotate(f'{height}%', xy=(bar.get_x() + bar.get_width() / 2, height),
                    xytext=(0, 4), textcoords="offset points", ha='center', fontsize=9, fontweight='bold')

plt.tight_layout()
plt.show()
```
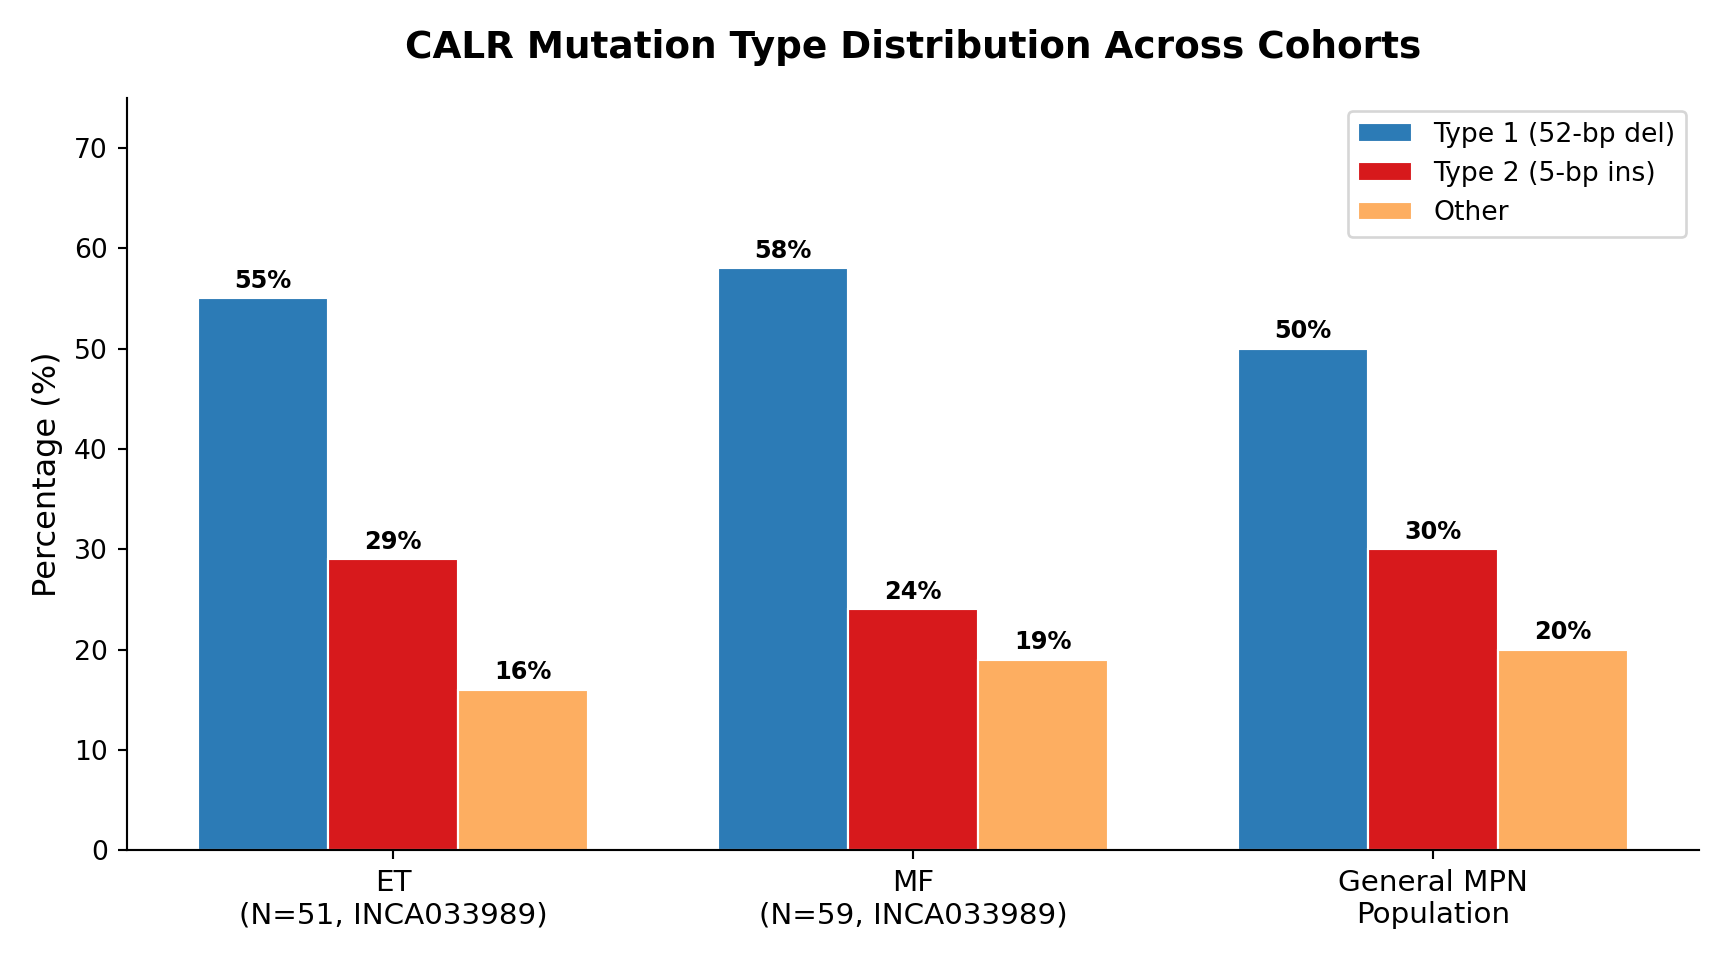
All CALR exon 9 mutations — whether Type 1 (52-bp deletion), Type 2 (5-bp insertion), or other variants — generate a shared C-terminal neoantigen. The mutant protein loses its KDEL endoplasmic reticulum retention motif, allowing it to traffic to the cell surface in complex with MPL, where it drives constitutive JAK-STAT signaling and malignant hematopoiesis.
::: {.callout-important}
## Clinical Relevance of CALR Mutation Types
Type 1 mutations carry the highest risk of transformation from ET to myelofibrosis and have shown the strongest responses to INCA033989 in clinical trials (100% hematologic response rate in ET). Type 2 and other mutations still respond but at lower rates (~58%), highlighting the need for therapies with equipotent activity across all mutation types.
:::
---
# Therapeutic Modalities Overview {#sec-overview}
```{r}
#| label: tbl-landscape
#| tbl-cap: "CALR-Directed Therapeutic Landscape — Current Status (March 2026)"
landscape <- tibble::tribble(
  ~Therapy,          ~Developer,           ~Modality,                   ~Stage,                    ~Target_Population,               ~Key_Milestone,
  "INCA033989",      "Incyte",             "Fc-silenced IgG1 mAb",     "Phase 1 (→ Phase 3)",     "ET & MF (mutCALR)",              "FDA BTD (ET Type 1); Phase 3 planned mid-2026",
  "DMR-001",         "Damora Therapeutics","Anti-mutCALR mAb (SC)",     "IND-enabling",            "ET & MF (mutCALR)",              "IND submission mid-2026; Phase 1 POC 2027",
  "INCA035784",      "Incyte",             "mutCALR×CD3 bispecific",    "Phase 1",                 "MF & ET (mutCALR)",              "Phase 1 enrollment started 2025",
  "JNJ-88549968",    "Johnson & Johnson",  "CALRmut×CD3 bispecific",    "Phase 1",                 "MF & ET (mutCALR)",              "Phase 1 ongoing (NCT06150157)",
  "CAR-T (huAB2)",   "UCL / Oxford",       "Anti-mutCALR CAR-T",       "Preclinical",             "MF (mutCALR)",                   "Phase 1 planned",
  "CAR-T (Pesini)",  "Academic",           "Anti-mCALR CAR-T (4-1BB)", "Preclinical",             "MPN (mutCALR)",                  "Preclinical validation 2026",
  "CALRLong36 Vax",  "Mt. Sinai / Denmark","Peptide vaccine",          "Phase 1 (completed)",     "MPN (mutCALR)",                  "Immune response but no clinical response",
  "CALR+Ipi Vax",    "Academic",           "Vaccine + ipilimumab",     "Phase 1 (discontinued)",  "MPN (CALR & JAK2)",              "Discontinued — no allele burden reduction"
)

landscape |>
  gt() |>
  tab_header(
    title = md("**CALR-Directed Therapeutic Landscape**"),
    subtitle = md("*Status as of March 2026*")
  ) |>
  cols_label(
    Therapy = "Agent",
    Developer = "Developer",
    Modality = "Modality",
    Stage = "Stage",
    Target_Population = "Population",
    Key_Milestone = "Key Milestone"
  ) |>
  tab_style(
    style = cell_text(weight = "bold"),
    locations = cells_column_labels()
  ) |>
  tab_style(
    style = cell_fill(color = "#dff0d8"),
    locations = cells_body(rows = Stage %in% c("Phase 1 (→ Phase 3)"))
  ) |>
  tab_style(
    style = cell_fill(color = "#d9edf7"),
    locations = cells_body(rows = Stage == "Phase 1")
  ) |>
  tab_style(
    style = cell_fill(color = "#fcf8e3"),
    locations = cells_body(rows = Stage == "IND-enabling")
  ) |>
  tab_style(
    style = cell_fill(color = "#f2f2f2"),
    locations = cells_body(rows = Stage == "Preclinical")
  ) |>
  tab_style(
    style = cell_fill(color = "#f2dede"),
    locations = cells_body(rows = grepl("completed|discontinued", Stage))
  ) |>
  tab_style(
    style = cell_text(size = px(11)),
    locations = cells_body()
  ) |>
  tab_footnote(
    footnote = "BTD = Breakthrough Therapy Designation; SC = Subcutaneous; mAb = Monoclonal Antibody; POC = Proof of Concept",
    locations = cells_column_labels(columns = Key_Milestone)
  )
```
---
# Monoclonal Antibodies {#sec-mabs}
## INCA033989 (Incyte) {#sec-inca033989}
INCA033989 is the most clinically advanced CALR-directed therapy and represents a potential paradigm shift for mutCALR-driven MPNs. It is a fully human, Fc-silenced IgG1 monoclonal antibody that selectively inhibits oncogenic signaling by binding the mutCALR neopeptide complexed with MPL on the cell surface. By inducing dynamin-dependent endocytosis of the INCA033989/mutCALR/MPL complex, it inhibits constitutive JAK-STAT activation while sparing normal (wild-type CALR) hematopoiesis.
### Mechanism of Action
The Fc-silenced design avoids antibody-dependent cellular cytotoxicity (ADCC) and complement-dependent cytotoxicity (CDC), meaning the therapeutic effect derives from **signal blockade and receptor internalization** rather than immune effector-mediated cell killing. This has important clinical implications: unlike T-cell engaging approaches, INCA033989 does not carry risk of cytokine release syndrome.
### Clinical Program
Two multicenter, open-label Phase 1 studies are evaluating INCA033989:
- **INCA33989-101** (NCT05936359)
- **INCA33989-102** (NCT06034002)
These studies evaluate INCA033989 as monotherapy and in combination with ruxolitinib across approximately 455 patients with mutCALR-expressing MPNs.
### ET Data (ASH 2025 Update, N=51)
```{r}
#| label: tbl-et-efficacy
#| tbl-cap: "INCA033989 Efficacy in Essential Thrombocythemia (ASH 2025, N=51)"
et_efficacy <- tibble::tribble(
  ~Endpoint,                                          ~Result,              ~Detail,
  "Overall Response Rate (CHR + PHR)",                "80% (41/51)",        "Median time to onset: 21 days",
  "Complete Hematologic Response (CHR)",              "73% (37/51)",        "Platelets <400 + WBC <10",
  "CHR at doses ≥400 mg",                            "83% (30/36)",        "Higher dose = greater response",
  "Durable hematologic response (≥12 wk)",           "51% (21/41)",        "Among evaluable patients",
  "Durable CHR (≥12 wk)",                            "39% (16/41)",        "Median onset: 15 days",
  "Any mutCALR VAF reduction",                       "90% (37/41)",        "VAF reductions range 2–91%",
  "Molecular response (≥20% VAF reduction)",          "44% (18/41)",        "Correlates with durable response",
  "Partial molecular response (≥50% VAF reduction)",  "20% (8/41)",         "Deep molecular activity",
  "Durable remission with molecular response",       "88% (14/16)",        "Among durable remitters",
  "Discontinued concomitant cytoreductive therapy",   "67% (20/30)",        "Of those on HU/anagrelide"
)

et_efficacy |>
  gt() |>
  tab_header(
    title = md("**Hematologic & Molecular Responses — ET Cohort**"),
    subtitle = "Data cutoff: May 8, 2025 (ASH 2025)"
  ) |>
  cols_label(
    Endpoint = "Endpoint",
    Result = "Result",
    Detail = "Notes"
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(rows = c(1, 2, 3))) |>
  tab_style(style = cell_fill(color = "#d9edf7"), locations = cells_body(rows = c(4, 5))) |>
  tab_style(style = cell_fill(color = "#fcf8e3"), locations = cells_body(rows = c(6, 7, 8, 9))) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = "CHR = platelets <400×10⁹/L + leukocytes <10×10⁹/L; PHR = platelets <600×10⁹/L + leukocytes <10×10⁹/L",
    locations = cells_body(columns = Endpoint, rows = 1)
  )
```
### MF Data (ASH 2025, Monotherapy N=47, Combination N=14)
```{r}
#| label: tbl-mf-efficacy
#| tbl-cap: "INCA033989 in Myelofibrosis — Monotherapy & Combination with Ruxolitinib"
mf_data <- tibble::tribble(
  ~Endpoint,                               ~Monotherapy_N47,            ~Combo_Rux_N14,
  "Median age, years (range)",             "60 (34–76)",                "62 (51–82)",
  "Median exposure, weeks (range)",        "28 (0.4–85)",               "19 (4–40)",
  "Continued on treatment",               "85%",                       "93%",
  "SVR25 at Week 24",                      "41.7% (15/36)",             "50% (2/4)",
  "SVR35 at Week 24",                      "33.3% (12/36)",             "25% (1/4)",
  "SVR35 (JAKi-naïve subset)",            "57.1%",                     "—",
  "Major/minor anemia response",          "56% (12/21 evaluable)",     "13% (1/8)",
  "TSS50 at Week 24",                      "60%",                       "—",
  "Mean TSS Δ from baseline (Wk 12)",      "–13.2",                     "–12.0",
  "Any VAF reduction",                     "Observed in majority",      "75% (6/8)",
  "Molecular response (≥20% VAF↓)",        "Observed in subset",        "13% (1/8)",
  "DLTs observed",                         "None",                      "None",
  "MTD reached",                           "No",                        "No"
)

mf_data |>
  gt() |>
  tab_header(
    title = md("**Myelofibrosis Efficacy — INCA033989**"),
    subtitle = "Phase 1 dose escalation (data cutoff: September 25, 2025)"
  ) |>
  cols_label(
    Endpoint = "Endpoint",
    Monotherapy_N47 = md("**Monotherapy (N=47)**"),
    Combo_Rux_N14 = md("**+ Ruxolitinib (N=14)**")
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(rows = c(4, 5, 6))) |>
  tab_style(style = cell_fill(color = "#d9edf7"), locations = cells_body(rows = c(7, 8, 9))) |>
  tab_style(style = cell_fill(color = "#fcf8e3"), locations = cells_body(rows = c(10, 11))) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = "SVR = Spleen Volume Reduction; TSS = Total Symptom Score; JAKi = JAK inhibitor; DLT = Dose-Limiting Toxicity; MTD = Maximum Tolerated Dose",
    locations = cells_column_labels(columns = Endpoint)
  )
```
### Benchmarking Against Approved JAK Inhibitors
```{r}
#| label: tbl-benchmark
#| tbl-cap: "INCA033989 MF Efficacy vs. Benchmark Frontline JAK Inhibitor Trials"
benchmark <- tibble::tribble(
  ~Study_Drug,                    ~Setting,                          ~SVR35_Wk24,  ~TSS50,    ~Reference,
  "INCA033989 (all MF mono)",    "JAKi R/R/I or ineligible",        "33.3%",      "60%",     "ASH 2025 (Abs #484)",
  "INCA033989 (JAKi-naïve)",     "JAKi-ineligible subset",          "57.1%",      "60%",     "ASH 2025 (Abs #484)",
  "COMFORT / Ruxolitinib",       "Int-2 or high risk MF",           "41.9%",      "45.9%",   "NEJM 2012; 366:799–807",
  "JAKARTA / Fedratinib",        "Untreated Int-2 or high risk MF", "36.5%",      "36.3%",   "Blood 2013; 122:393",
  "PERSIST-1 / Pacritinib",      "Int-1/2 or high risk MF",         "19%",        "19%",     "JAMA Oncol 2018; 4(652)",
  "SIMPLIFY-1 / Momelotinib",    "Int-1/2 or high risk MF",         "26.5%",      "28.4%",   "JCO 2017; 35(34)"
)

benchmark |>
  gt() |>
  tab_header(
    title = md("**INCA033989 MF Efficacy in Context of Approved JAK Inhibitors**"),
    subtitle = "Spleen volume and symptom responses at Week 24"
  ) |>
  cols_label(
    Study_Drug = "Study / Drug",
    Setting = "Setting",
    SVR35_Wk24 = "SVR35 @ Wk 24",
    TSS50 = "TSS50",
    Reference = "Reference"
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(rows = c(1, 2))) |>
  tab_style(style = cell_fill(color = "#fce4d6"), locations = cells_body(rows = 3)) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = md("**Caution**: Cross-trial comparisons are limited by differences in patient populations, disease characteristics, and study design. INCA033989 data are from Phase 1 dose escalation; JAK inhibitor data are from randomized Phase 3 trials. INCA033989 is restricted to mutCALR patients (~30% of MF)."),
    locations = cells_column_labels(columns = SVR35_Wk24)
  )
```
### Regulatory Milestones
- **December 2025**: FDA granted **Breakthrough Therapy Designation** for ET harboring Type 1 CALR mutation (R/I to ≥1 cytoreductive therapy)
- **2026 (planned)**: Phase 3 registrational program in ET (all CALR mutation types)
- **2026 (planned)**: Registrational program initiation in MF
---
## DMR-001 (Damora Therapeutics) {#sec-dmr001}
Damora Therapeutics (NASDAQ: DMRA, formerly Galecto/GLTO) is developing DMR-001, a potentially **best-in-class** anti-mutCALR monoclonal antibody with several key differentiating features.
### Key Differentiators
```{r}
#| label: tbl-dmr001
#| tbl-cap: "DMR-001 vs. INCA033989 — Preclinical Differentiation"
dmr_comp <- tibble::tribble(
  ~Feature,                          ~DMR_001,                                      ~INCA033989,
  "Developer",                       "Damora Therapeutics (Paragon)",                "Incyte",
  "Modality",                        "Anti-mutCALR mAb",                            "Anti-mutCALR mAb (Fc-silenced IgG1)",
  "Route of administration",        "Subcutaneous",                                "Intravenous (Q2W)",
  "Dosing frequency",               "Infrequent (extended half-life)",              "Every 2 weeks",
  "Type 2 mutCALR potency",         "~10-fold greater vs. reference molecule",      "Lower activity in Type 2 vs Type 1",
  "Type 1 mutCALR activity",        "Active (preclinical)",                         "100% response rate in ET (clinical)",
  "CALR mutation coverage",         "Designed for all mutation types",              "BTD for Type 1; activity in all types",
  "Half-life extension",            "Validated half-life extension technology",      "Standard IgG1 half-life",
  "Clinical stage",                 "IND planned mid-2026",                         "Phase 1 (→ Phase 3 planned 2026)",
  "Key funding",                    "$285M Series C + $316M public (2025–2026)",    "Incyte internal"
)

dmr_comp |>
  gt() |>
  tab_header(
    title = md("**DMR-001 vs. INCA033989 Comparison**"),
    subtitle = "Based on available preclinical and public disclosures"
  ) |>
  cols_label(
    Feature = "Feature",
    DMR_001 = md("**DMR-001**"),
    INCA033989 = md("**INCA033989**")
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#e8daef"), locations = cells_body(rows = c(3, 4, 5))) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = "10-fold potency claim based on Damora internal preclinical data vs. a 'reference molecule in clinical development'",
    locations = cells_body(columns = Feature, rows = 5)
  )
```
### Damora Pipeline
Damora's broader pipeline includes:
- **DMR-001**: Lead anti-mutCALR mAb — IND submission mid-2026
- **DMR-002**: Second therapeutic candidate — IND/CTA planned H2 2026
- **DMR-003**: Third program — regulatory submission planned 2027
- **Additional discovery programs** in the mutCALR space
The company raised approximately **$601 million** (combined $285M Series C + $316M public offering) and expects financial runway into 2029, supporting Phase 3 development of DMR-001.
::: {.callout-tip}
## Clinical Perspective
DMR-001's subcutaneous formulation and infrequent dosing could be a significant practical advantage for patients with chronic disease requiring long-term therapy. If preclinical potency advantages against Type 2 mutations translate clinically, DMR-001 could address a key limitation of INCA033989.
:::
---
# T-Cell Engaging Bispecific Antibodies {#sec-tce}
## INCA035784 (Incyte) {#sec-inca035784}
INCA035784 is Incyte's second CALR-directed asset — a mutCALR×CD3 T-cell redirecting bispecific antibody designed to engage the adaptive immune system for direct killing of mutCALR-expressing cells.
### Key Features
- **Equipotent activity** against all CALR mutation types (Type 1, Type 2, and other variants)
- **Binds a different epitope** than INCA033989, enabling potential complementary or sequential use
- Induces T-cell activation, proliferation, and target cell cytotoxicity in preclinical models
- Demonstrated killing of patient-derived CD34+ cells from both Type 1 and Type 2 MF patients
- **Low cytokine release** profile in PBMC-based assays
### Clinical Development
- **NCT07008118** — Phase 1, open-label, multicenter study
- Enrollment: ~120 patients with MPN carrying CALR exon 9 mutations
- Population: DIPSS+ Int-2/high-risk MF with prior JAKi; ET resistant/refractory to ≥2 prior lines
- Dosing: IV infusions in 28-day cycles
---
## JNJ-88549968 (Johnson & Johnson / Janssen) {#sec-jnj}
JNJ-88549968 is a competing first-in-class CALRmut×CD3 T-cell redirecting bispecific antibody developed by Janssen Research & Development.
### Preclinical Profile
- Selectively binds mutCALR cell lines with **no measurable binding** to CALR wild-type cells
- Induces concentration-dependent cytotoxicity of patient-derived CALRmut CD34+ cells
- Activity demonstrated across all known CALR mutation types
- Soluble mutCALR protein in patient plasma does **not interfere** with antibody activity
- Extended survival in disseminated leukemia mouse models
### Clinical Status
- **NCT06150157** — Phase 1 first-in-human trial
- Dose escalation (Part 1) to determine RP2D
- Cohort expansion (Part 2) for safety characterization
- Includes both MF and ET patients with CALR mutations
::: {.callout-note}
## Competitive Dynamics in T-Cell Engagers
Both INCA035784 and JNJ-88549968 are entering Phase 1 trials with limited publicly available clinical data. Key differentiators to watch include CRS rates, depth of molecular response, and whether T-cell engagement can achieve deeper clonal elimination than signal blockade with INCA033989.
:::
---
# CAR-T Cell Therapies {#sec-cart}
Multiple academic groups are developing chimeric antigen receptor T-cell therapies targeting mutant calreticulin.
## UCL/Oxford Program (Rampotas, Psaila, Pule, Roddie)
This program, led by investigators at University College London and the University of Oxford, has generated the most comprehensive preclinical dataset for anti-mutCALR CAR-T therapy.
### huAB2 CAR-T
- **huAB2** is a high-affinity, humanized mutCALR-specific antibody used as the targeting domain
- Second-generation CAR construct with 4-1BB co-stimulatory domain
- Demonstrated selective killing of mutCALR+ cells while preserving normal hematopoiesis
- In patient-derived xenograft models: eradicated MPN-propagating CALRmut HSCs without antigen escape
- Validated efficacy in the **fibrotic tumor microenvironment** characteristic of MF (TGFβ-rich)
- Phase 1 first-in-human trial planned
## Additional CAR-T Programs
Pesini *et al.* (2026) independently validated anti-mCALR CAR-T cells, demonstrating efficacy against both established cell lines and patient-derived cells in orthotopic xenograft models. Transcriptomic profiling identified apoptosis resistance mechanisms, supporting combination with BH3 mimetics such as venetoclax.
::: {.callout-important}
## CAR-T: Curative Potential but Practical Challenges
CAR-T therapy offers the theoretical advantage of deep, durable clonal elimination — potentially curative intent. However, the MPN bone marrow microenvironment (fibrosis, TGFβ, chronic inflammation) and the low surface expression of MPL/mutCALR on HSCs present unique challenges. Manufacturing logistics, cost, and the chronic nature of MPNs also raise questions about scalability compared to off-the-shelf antibody approaches.
:::
---
# Vaccine Approaches {#sec-vaccines}
## CALRLong36 Peptide Vaccine (NCT03566446)
The first therapeutic cancer vaccination trial targeting mutant CALR was conducted in Denmark with the CALRLong36 peptide — a 36-amino acid peptide spanning the entire mutant C-terminus, administered with montanide adjuvant.
```{r}
#| label: tbl-vaccine
#| tbl-cap: "CALR Vaccine Clinical Trials — Summary of Results"
vaccine_data <- tibble::tribble(
  ~Trial,                       ~N,   ~Design,                                     ~Immune_Response,           ~Clinical_Response,           ~Status,
  "CALRLong36 (NCT03566446)",   10,   "Peptide + montanide, 15 doses over 1 year", "8/10 (80%) T-cell response","0/10 (0%)",                  "Completed — no clinical efficacy",
  "CALR/JAK2 + Ipi (NCT05444530)", 14,"Dual vaccine + ipilimumab",                "35.7% CALR-specific",       "0/14 (no allele reduction)", "Discontinued early",
  "Mt. Sinai Vaccine (NCT05025488)", 10,"mutCALR peptide + KLH + Poly-ICLC",       "Ongoing assessment",        "Ongoing assessment",         "Enrolling at Mount Sinai"
)

vaccine_data |>
  gt() |>
  tab_header(
    title = md("**CALR-Directed Vaccine Trials**"),
    subtitle = "Clinical trial outcomes and status"
  ) |>
  cols_label(
    Trial = "Trial",
    N = "N",
    Design = "Design",
    Immune_Response = "Immune Response",
    Clinical_Response = "Clinical Response",
    Status = "Status"
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#f2dede"), locations = cells_body(rows = c(1, 2))) |>
  tab_style(style = cell_fill(color = "#d9edf7"), locations = cells_body(rows = 3)) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = "KLH = Keyhole Limpet Hemocyanin; Ipi = Ipilimumab; Poly-ICLC = polyinosinic-polycytidylic acid adjuvant",
    locations = cells_column_labels(columns = Design)
  )
```
### Why Have Vaccines Underperformed?
Despite robust immunogenicity (T-cell responses in 80% of vaccinated patients), peptide vaccines have failed to produce clinical or molecular responses. Several mechanisms have been proposed:
1. **Failure of T-cell trafficking to bone marrow** — TCR sequencing demonstrated that CALR-specific T cells expanded in peripheral blood but did not enrich in bone marrow aspirates
2. **MHC Class I downregulation** — Mutant CALR disrupts the peptide-loading complex, reducing HLA-I expression and impairing neoantigen presentation
3. **Immunosuppressive microenvironment** — Chronic MPN-related inflammation may suppress effector T-cell function at the tumor site
4. **Inadequate adjuvant stimulation** — Montanide alone may not overcome immune tolerance in a chronic disease setting
---
# Mechanism of Action Comparison {#sec-moa}
```{r}
#| label: tbl-moa-comparison
#| tbl-cap: "Comprehensive MOA Comparison of CALR-Directed Therapeutic Modalities"
moa_table <- tibble::tribble(
  ~Feature,                       ~Naked_mAb,                              ~TCE_Bispecific,                          ~CAR_T,                                   ~Vaccine,
  "Primary mechanism",           "Signal blockade + receptor internalization", "T-cell-mediated cytotoxicity",          "T-cell-mediated cytotoxicity",           "Endogenous T-cell priming",
  "Target engagement",           "mutCALR/MPL complex on cell surface",       "mutCALR on tumor + CD3 on T cells",     "mutCALR on tumor cell surface",          "Peptide-MHC presentation",
  "Immune effector cells",       "None (Fc-silenced)",                        "Polyclonal T cells (redirected)",       "Engineered autologous T cells",          "Endogenous CD4+/CD8+ T cells",
  "MHC restriction",             "No",                                        "No",                                    "No",                                     "Yes (HLA-dependent)",
  "CRS risk",                    "Minimal",                                   "Moderate–High",                         "Moderate–High",                          "Minimal",
  "Disease modification",        "VAF reduction, HSPC depletion",             "Clonal elimination (theoretical)",      "Deep clonal elimination (theoretical)",  "Limited (immune priming only)",
  "Curative potential",          "Low (chronic therapy)",                     "Moderate",                              "High (one-time treatment)",              "Low",
  "Off-the-shelf",               "Yes",                                       "Yes",                                   "No (autologous manufacturing)",          "Yes",
  "Dosing convenience",          "IV Q2W or SC infrequent",                   "IV Q2–4W (step-up dosing)",             "Single infusion + monitoring",           "Multiple injections over months",
  "Activity across CALR types",  "Type 1 > Type 2 (INCA033989)",             "Equipotent (INCA035784)",               "Mutation-type dependent",                "Shared neoantigen (all types)",
  "Bone marrow penetration",     "Demonstrated (IHC evidence)",               "Theoretical (T-cell trafficking)",      "Demonstrated in xenograft models",       "Failed in clinical trial",
  "Key limitation",              "Chronic dosing; Type 2 response gap",       "CRS; limited clinical data",            "Manufacturing; MF microenvironment",     "No clinical responses observed",
  "Most advanced agent",         "INCA033989 (Phase 1→3) / DMR-001 (IND)",   "INCA035784 / JNJ-88549968 (Phase 1)",   "huAB2 (preclinical)",                    "CALRLong36 (completed Phase 1)"
)

moa_table |>
  gt() |>
  tab_header(
    title = md("**Mechanism of Action Comparison**"),
    subtitle = "CALR-Directed Therapeutic Modalities for MPNs"
  ) |>
  cols_label(
    Feature = "",
    Naked_mAb = md("**Monoclonal Antibody**"),
    TCE_Bispecific = md("**T-Cell Engager**"),
    CAR_T = md("**CAR-T Cell**"),
    Vaccine = md("**Vaccine**")
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_text(weight = "bold", size = px(11)), locations = cells_body(columns = Feature)) |>
  tab_style(style = cell_fill(color = "#eaf2f8"), locations = cells_body(columns = Naked_mAb)) |>
  tab_style(style = cell_fill(color = "#fdf2e9"), locations = cells_body(columns = TCE_Bispecific)) |>
  tab_style(style = cell_fill(color = "#fef9e7"), locations = cells_body(columns = CAR_T)) |>
  tab_style(style = cell_fill(color = "#eafaf1"), locations = cells_body(columns = Vaccine)) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  cols_width(
    Feature ~ px(180),
    everything() ~ px(200)
  ) |>
  tab_footnote(
    footnote = "CRS = Cytokine Release Syndrome; MHC = Major Histocompatibility Complex; HSPC = Hematopoietic Stem/Progenitor Cell; IHC = Immunohistochemistry",
    locations = cells_column_labels(columns = Feature)
  )
```
```{python}
#| label: fig-development-timeline
#| fig-cap: "Development Timeline of CALR-Directed Therapies"
import matplotlib.pyplot as plt
import matplotlib.patches as mpatches
import numpy as np

fig, ax = plt.subplots(figsize=(14, 7))

therapies = [
    ("INCA033989\n(Incyte)", "Monoclonal Ab", 2022, 2026.5, "#2c7bb6",
     ["Phase 1\n(2023)", "EHA\n(2025)", "ASH\n(2025)", "BTD\n(Dec 2025)", "Phase 3\n(mid-2026)"]),
    ("DMR-001\n(Damora)", "Monoclonal Ab", 2024, 2027.5, "#5499c7",
     ["Preclinical", "Galecto Acq\n(Nov 2025)", "IND\n(mid-2026)", "Phase 1 POC\n(2027)"]),
    ("INCA035784\n(Incyte)", "T-Cell Engager", 2024, 2026.5, "#d7191c",
     ["Preclinical", "EHA Poster\n(Jun 2025)", "Phase 1\n(2025)"]),
    ("JNJ-88549968\n(J&J/Janssen)", "T-Cell Engager", 2022, 2026, "#e74c3c",
     ["Discovery\n(ASH 2023)", "Phase 1\n(Dec 2023)", "Ongoing"]),
    ("CAR-T\n(UCL/Oxford)", "CAR-T", 2023, 2027, "#fdae61",
     ["Preclinical", "ASH\n(2024)", "BioRxiv\n(2026)", "Phase 1\n(planned)"]),
    ("CALRLong36\nVaccine", "Vaccine", 2018, 2023, "#1a9641",
     ["Phase 1\n(NCT03566446)", "Completed\n(No response)"]),
    ("CALR/JAK2\n+ Ipilimumab", "Vaccine", 2022, 2025, "#82c971",
     ["Phase 1\n(NCT05444530)", "Discontinued"]),
]

y_positions = list(range(len(therapies)))
modality_colors = {"Monoclonal Ab": "#2c7bb6", "T-Cell Engager": "#d7191c",
                   "CAR-T": "#fdae61", "Vaccine": "#1a9641"}

for i, (name, modality, start, end, color, milestones) in enumerate(therapies):
    ax.barh(i, end - start, left=start, height=0.5, color=color, alpha=0.7, edgecolor='white', linewidth=1.2)
    ax.text(start - 0.1, i, name, va='center', ha='right', fontsize=9, fontweight='bold')

ax.set_yticks([])
ax.set_xlabel('Year', fontsize=12, fontweight='bold')
ax.set_title('Development Timeline of CALR-Directed Therapies', fontsize=14, fontweight='bold', pad=15)
ax.set_xlim(2017.5, 2028)
ax.spines['top'].set_visible(False)
ax.spines['right'].set_visible(False)
ax.spines['left'].set_visible(False)

# Add current date marker
ax.axvline(x=2026.21, color='#333333', linestyle='--', linewidth=1.5, alpha=0.7)
ax.text(2026.21, len(therapies) - 0.3, 'Today\n(Mar 2026)', ha='center', fontsize=8,
        fontweight='bold', color='#333333')

# Legend
legend_patches = [mpatches.Patch(color=c, label=m, alpha=0.7) for m, c in modality_colors.items()]
ax.legend(handles=legend_patches, loc='lower right', frameon=True, facecolor='white',
          edgecolor='#cccccc', fontsize=10)

plt.tight_layout()
plt.show()
```
---
# Molecular Characterization & Disease Modification {#sec-molecular}
## Evidence for Disease Modification with INCA033989
Comprehensive clinicogenomic and histological analyses (ASH 2025, Abstract #71) across 110 patients (51 ET, 59 MF) provide compelling evidence for disease-modifying activity:
```{r}
#| label: tbl-disease-modification
#| tbl-cap: "Evidence for Disease Modification with INCA033989"
dm_evidence <- tibble::tribble(
  ~Analysis_Method,           ~Finding,                                              ~Clinical_Implication,
  "NGS (37-gene panel)",     "95% of ET responders had VAF reduction (range 2–91%)", "Molecular correlate of hematologic response",
  "NGS (37-gene panel)",     "R² = 0.97 correlation BM vs. PB VAF",                 "Peripheral blood monitoring sufficient",
  "Single-cell multi-omic",  "Rapid reduction of mutCALR+ HSPCs by cycle 3 (6 wk)",  "Direct targeting of disease-initiating cells",
  "IHC (CD61 + mutCALR Ab)", "Decreased total MK density",                            "Reduction of aberrant megakaryopoiesis",
  "IHC (CD61 + mutCALR Ab)", "Decreased mutCALR+ MKs, increased mutCALR– MKs",       "Shift from mutant to normal hematopoiesis",
  "Clinical correlation",    "88% of durable remitters achieved molecular response",  "Deep responses associate with durability"
)

dm_evidence |>
  gt() |>
  tab_header(
    title = md("**Multidimensional Evidence for Disease Modification**"),
    subtitle = "INCA033989 in ET and MF — ASH 2025"
  ) |>
  cols_label(
    Analysis_Method = "Method",
    Finding = "Key Finding",
    Clinical_Implication = "Clinical Implication"
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body()) |>
  tab_footnote(
    footnote = "NGS = Next-Generation Sequencing; BM = Bone Marrow; PB = Peripheral Blood; HSPC = Hematopoietic Stem/Progenitor Cell; MK = Megakaryocyte; IHC = Immunohistochemistry",
    locations = cells_column_labels(columns = Analysis_Method)
  )
```
## Co-Occurring Mutations
```{python}
#| label: fig-comutations
#| fig-cap: "Co-occurring somatic mutations in CALR-mutant ET vs. MF patients"
import matplotlib.pyplot as plt
import numpy as np

genes = ['ASXL1', 'TET2', 'EZH2', 'Other\nvariants']
et_freq = [5, 16, 2, 10]
mf_freq = [42, 31, 12, 40]

x = np.arange(len(genes))
width = 0.35

fig, ax = plt.subplots(figsize=(9, 5))
bars1 = ax.bar(x - width/2, et_freq, width, label='ET (33% with co-mutations)', color='#3498db', alpha=0.85, edgecolor='white')
bars2 = ax.bar(x + width/2, mf_freq, width, label='MF (83% with co-mutations)', color='#e74c3c', alpha=0.85, edgecolor='white')

ax.set_ylabel('Frequency (%)', fontsize=12)
ax.set_title('Co-Occurring Mutations in CALR-Mutant Patients', fontsize=14, fontweight='bold', pad=15)
ax.set_xticks(x)
ax.set_xticklabels(genes, fontsize=11)
ax.legend(frameon=True, facecolor='white', edgecolor='#cccccc', fontsize=10)
ax.set_ylim(0, 55)
ax.spines['top'].set_visible(False)
ax.spines['right'].set_visible(False)

for bars in [bars1, bars2]:
    for bar in bars:
        height = bar.get_height()
        ax.annotate(f'{height}%', xy=(bar.get_x() + bar.get_width() / 2, height),
                    xytext=(0, 4), textcoords="offset points", ha='center', fontsize=9, fontweight='bold')

plt.tight_layout()
plt.show()
```
::: {.callout-tip}
## Clinical Insight
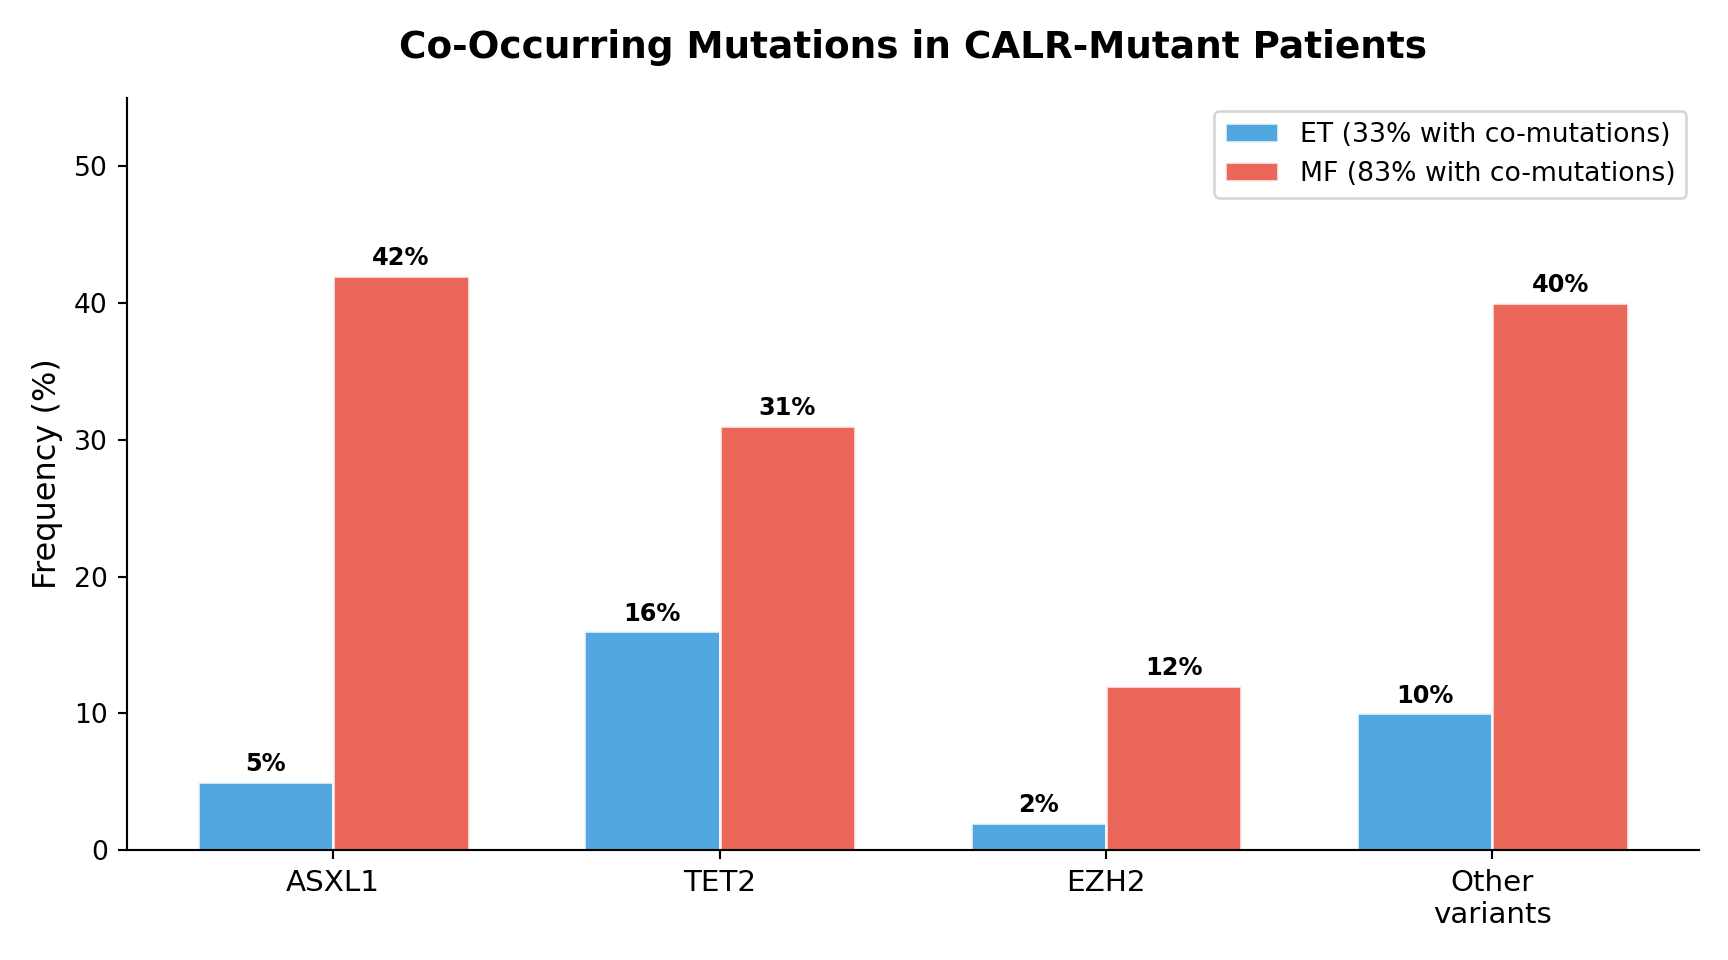
The dramatically higher co-mutation rate in MF (83%, range 0–9 per patient) compared to ET (33%, range 0–3) reflects the genomic complexity acquired during disease progression. Importantly, molecular responses to INCA033989 occurred across a range of baseline VAFs and in patients with co-occurring mutations, suggesting broad applicability. The high rate of ASXL1 co-mutation in MF (42%) is particularly relevant given its association with adverse prognosis and inferior JAK inhibitor response.
:::
---
# Safety Landscape {#sec-safety}
```{r}
#| label: tbl-safety-comparison
#| tbl-cap: "Safety Profiles Across CALR-Directed Therapies"
safety_comp <- tibble::tribble(
  ~AE_Category,                    ~INCA033989_ET,      ~INCA033989_MF_mono, ~INCA033989_MF_combo,  ~TCE_Expected,           ~CAR_T_Expected,
  "Any TEAE",                      "94%",               "89%",               "86%",                 "Expected high",         "Expected high",
  "Grade ≥3 TEAE",                "33%",               "43%",               "50%",                 "Moderate–High",         "Moderate–High",
  "Fatigue",                       "28%",               "Common",            "Common",              "Expected",              "Expected",
  "Anemia",                        "18% (with HU)",     "30% (Gr≥3: 17%)",  "36% (Gr≥3: 21%)",    "Possible",              "Possible",
  "Thrombocytopenia",             "0%",                "~15%",              "36% (Gr≥3: 7%)",     "Possible",              "Possible",
  "Neutropenia",                   "10%",               "Common",            "Common",              "Possible",              "Expected",
  "CRS",                           "Not observed",      "Not observed",      "Not observed",        "Expected (dose-dep.)",  "Expected",
  "DLTs",                          "None",              "None",              "None",                "TBD",                   "TBD",
  "MTD reached",                   "No",                "No",                "No",                  "TBD",                   "N/A",
  "Treatment continuation",       "94%",               "85%",               "93%",                 "TBD",                   "N/A (single dose)"
)

safety_comp |>
  gt() |>
  tab_header(
    title = md("**Safety Profile Comparison**"),
    subtitle = "CALR-directed therapies — observed and expected adverse events"
  ) |>
  cols_label(
    AE_Category = "Adverse Event",
    INCA033989_ET = md("**989 ET**<br>(N=51)"),
    INCA033989_MF_mono = md("**989 MF Mono**<br>(N=47)"),
    INCA033989_MF_combo = md("**989 MF Combo**<br>(N=14)"),
    TCE_Expected = md("**T-Cell Engager**<br>(Expected)"),
    CAR_T_Expected = md("**CAR-T**<br>(Expected)")
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(rows = AE_Category == "CRS")) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(rows = AE_Category == "DLTs")) |>
  tab_style(style = cell_text(size = px(10)), locations = cells_body()) |>
  tab_footnote(
    footnote = "989 = INCA033989; HU = Hydroxyurea; CRS = Cytokine Release Syndrome; DLT = Dose-Limiting Toxicity; MTD = Maximum Tolerated Dose; TBD = To Be Determined",
    locations = cells_column_labels(columns = AE_Category)
  )
```
---
# Future Directions & Clinical Perspectives {#sec-future}
## Emerging Questions
1. **Sequencing and combination strategies**: How will CALR-directed therapies integrate with existing JAK inhibitors? The INCA033989 + ruxolitinib combination data provide early proof-of-concept for add-on therapy in suboptimal responders.
2. **Type 2 mutation coverage**: DMR-001's claimed 10-fold potency advantage against Type 2 mutations could address a key gap if validated clinically. Head-to-head comparison data will be critical.
3. **Curative intent vs. chronic therapy**: Monoclonal antibodies appear positioned as chronic disease-modifying therapies, while CAR-T and T-cell engagers offer theoretical curative potential through deeper clonal elimination. The clinical relevance of this distinction remains to be established.
4. **Biomarker-guided therapy**: Baseline mutCALR VAF levels (0.22–0.34) in patients achieving durable remission with molecular response suggest potential for biomarker-driven patient selection.
5. **MPN disease continuum**: Can early CALR-directed intervention in ET prevent progression to myelofibrosis? This remains the most transformative unanswered question.
## Practical Considerations for Clinical Practice
```{r}
#| label: tbl-practical
#| tbl-cap: "Practical Considerations for CALR-Directed Therapy Selection"
practical <- tibble::tribble(
  ~Consideration,                 ~Current_Approach,                          ~Future_with_CALR_Therapy,
  "Diagnosis",                   "Standard MPN workup + CALR testing",       "CALR mutation type (1 vs 2) + VAF baseline",
  "First-line ET",               "HU, anagrelide, interferon",               "INCA033989 after R/I to cytoreduction (2026+)",
  "First-line MF",               "Ruxolitinib, fedratinib",                  "INCA033989 mono for JAKi-ineligible; combo for suboptimal responders",
  "Treatment monitoring",        "CBC, peripheral smear, BM biopsy",         "Peripheral blood mutCALR VAF (R² 0.97 with BM)",
  "Response assessment",         "ELN/IWG hematologic criteria",             "Molecular response (≥20% VAF reduction) as co-primary endpoint",
  "Transplant decision",         "DIPSS+, HCT-CI, donor availability",       "Molecular response depth may inform transplant timing",
  "Special populations",         "Young women (pregnancy), elderly",          "INCA033989: 1 pregnancy on trial; DMR-001 SC dosing convenience"
)

practical |>
  gt() |>
  tab_header(
    title = md("**Evolving Clinical Framework**"),
    subtitle = "Impact of CALR-directed therapies on MPN management"
  ) |>
  cols_label(
    Consideration = "Consideration",
    Current_Approach = "Current Approach",
    Future_with_CALR_Therapy = "With CALR-Directed Therapy"
  ) |>
  tab_style(style = cell_text(weight = "bold"), locations = cells_column_labels()) |>
  tab_style(style = cell_fill(color = "#eaf2f8"), locations = cells_body(columns = Current_Approach)) |>
  tab_style(style = cell_fill(color = "#dff0d8"), locations = cells_body(columns = Future_with_CALR_Therapy)) |>
  tab_style(style = cell_text(size = px(11)), locations = cells_body())
```
---
# Conclusions {#sec-conclusions}
The CALR-directed therapeutic landscape has undergone remarkable transformation since the identification of CALR mutations in 2013. Within a decade, we have moved from discovery to clinical validation and the threshold of registrational trials. Key takeaways:
- **INCA033989** is the clear front-runner, with FDA Breakthrough Therapy Designation, Phase 3 plans for ET (mid-2026), and a registrational MF program planned for 2026. The ASH 2025 data demonstrate clinically meaningful spleen, anemia, and symptom responses in MF that compare favorably to approved JAK inhibitors — particularly noteworthy in the JAKi-naïve subset (SVR35 of 57.1%). In ET, the 80% overall response rate, rapid onset (21 days), and evidence of disease modification through VAF reduction and clonal HSPC depletion represent a paradigm shift.
- **Damora Therapeutics (DMR-001)** offers a potentially differentiated approach with subcutaneous delivery, extended dosing intervals, and claimed potency advantages against Type 2 mutations. Clinical validation beginning mid-2026 will be critical to assess whether preclinical advantages translate to the clinic.
- **T-cell engaging bispecifics** (INCA035784, JNJ-88549968) are entering Phase 1, offering a complementary mechanism through direct T-cell-mediated killing. These agents carry theoretical advantages in clonal elimination depth but also CRS risk.
- **CAR-T therapies** represent the most ambitious curative strategy, with preclinical data demonstrating MPN stem cell eradication. Translation to clinical practice faces unique challenges in the MPN microenvironment.
- **Vaccine approaches** have demonstrated immunogenicity but clinical futility, likely due to failure of effector T-cell trafficking to bone marrow and mutCALR-mediated immune evasion.
The coming years will determine how these modalities integrate into clinical practice and whether CALR-directed therapy can truly alter the natural history of myeloproliferative neoplasms.
---
# References {#sec-references}
::: {#refs}
:::
Key references for this document:
1. Klampfl T, *et al.* Somatic mutations of calreticulin in myeloproliferative neoplasms. *N Engl J Med*. 2013;369(25):2379–2390.
2. Nangalia J, *et al.* Somatic CALR mutations in myeloproliferative neoplasms with nonmutated JAK2. *N Engl J Med*. 2013;369(25):2391–2405.
3. Reis ES, *et al.* Selective targeting of mutated calreticulin by the monoclonal antibody INCA033989. *Blood*. 2024;144.
4. Mascarenhas J, *et al.* INCA033989 in MF: Phase 1 results. *Blood*. 2025;146(Suppl 1):484.
5. Psaila B, *et al.* Molecular characterization of INCA033989-treated MPN patients. *Blood*. 2025;146(Suppl 1):71.
6. Kuchnio A, *et al.* Discovery of JNJ-88549968. *Blood*. 2023;142(Suppl 1):1777.
7. Holmström MO, *et al.* Therapeutic cancer vaccination against mutant CALR. *Front Immunol*. 2021;12:629651.
8. Rampotas A, *et al.* First-in-class CAR-T therapy against calreticulin-mutant neoplasms. *Blood*. 2024;144(Suppl 1):871.
9. Pesini C, *et al.* Mutant calreticulin enables potent and selective CAR-T cell therapy in preclinical models. *J Immunother Cancer*. 2026;14:e012706.
10. Verstovsek S, *et al.* COMFORT-I: Ruxolitinib in myelofibrosis. *N Engl J Med*. 2012;366:799–807.
11. Pardanani A, *et al.* JAKARTA: Fedratinib in myelofibrosis. *Blood*. 2013;122:393.
12. Mesa RA, *et al.* PERSIST-1: Pacritinib in myelofibrosis. *JAMA Oncol*. 2018;4(652).
13. Mesa RA, *et al.* SIMPLIFY-1: Momelotinib in myelofibrosis. *J Clin Oncol*. 2017;35(34).
---
*Document prepared using Quarto with R (gt, ggplot2, dplyr) and Python (matplotlib, pandas, numpy). Data sourced from published clinical trial results, ASH 2025 presentations, EHA 2025 abstracts, ClinicalTrials.gov registrations, and company press releases.*